
Treatments
After CAR-T Relapse: Records to Prepare Before Discussing Further Care in China
A practical CAR-T relapse record checklist for international patients preparing pathology, treatment, imaging and safety information before discussing further care in China.
MedToChina Editorial Team · 9 min read · October 13, 2026

Quick Summary
If cancer appears to return or progress after CAR-T cell therapy, the next clinical discussion usually depends on the details of the original disease, the CAR-T product and target, the response period, current test results, prior complications, and the patient's overall condition. For an international patient considering a discussion about further care in China, the most useful first step is usually to organize those records clearly.
This guide is a records-preparation guide, not a recommendation for another CAR-T treatment, a clinical trial, or any other therapy. A report that says relapse may need different clinical context depending on whether the original condition was lymphoma, leukemia, multiple myeloma, or another blood cancer. The treating clinical team determines which tests are necessary and what options, if any, are appropriate.
Reviewed October 13, 2026.
Why Records Matter After CAR-T Relapse
CAR-T therapy uses engineered T cells to recognize a target on cancer cells. It is used for selected blood cancers, but the treatment pathway and follow-up are highly disease-specific. When disease returns after an initial response, or does not respond as expected, a new clinical review may need to distinguish between disease progression, infection, treatment-related changes, a new complication, or another explanation for abnormal findings.
That is why a short message saying CAR-T failed is rarely enough for a meaningful cross-border discussion. The care team may need to understand the exact diagnosis at the time of infusion, target antigen, product name, cell collection and infusion dates, baseline disease burden, response assessments, and events since treatment. In some settings, clinicians may also consider whether the target antigen remains detectable, but the relevance and method of testing depend on the disease and clinical question.
For people traveling internationally, complete source records reduce the risk that key details are lost during translation, file transfer, or a change in care setting. They do not replace an in-person assessment, and they do not establish eligibility for a treatment in China.
Start With the Immediate Safety Question
New or worsening symptoms after CAR-T should be discussed promptly with the patient's treating oncology or hematology team, especially fever, shortness of breath, confusion, significant bleeding, severe weakness, rapidly enlarging masses, new neurological symptoms, or symptoms that make travel difficult. These can have many causes and require clinical assessment; a website checklist is not a substitute for urgent care.
Before arranging international travel, ask the current team whether the patient is medically stable for travel and whether care should be coordinated locally first. Do not stop, start, or change cancer medicines, infection prophylaxis, steroids, anticoagulants, or other prescribed drugs based on an online article.
The Core Record Set to Assemble
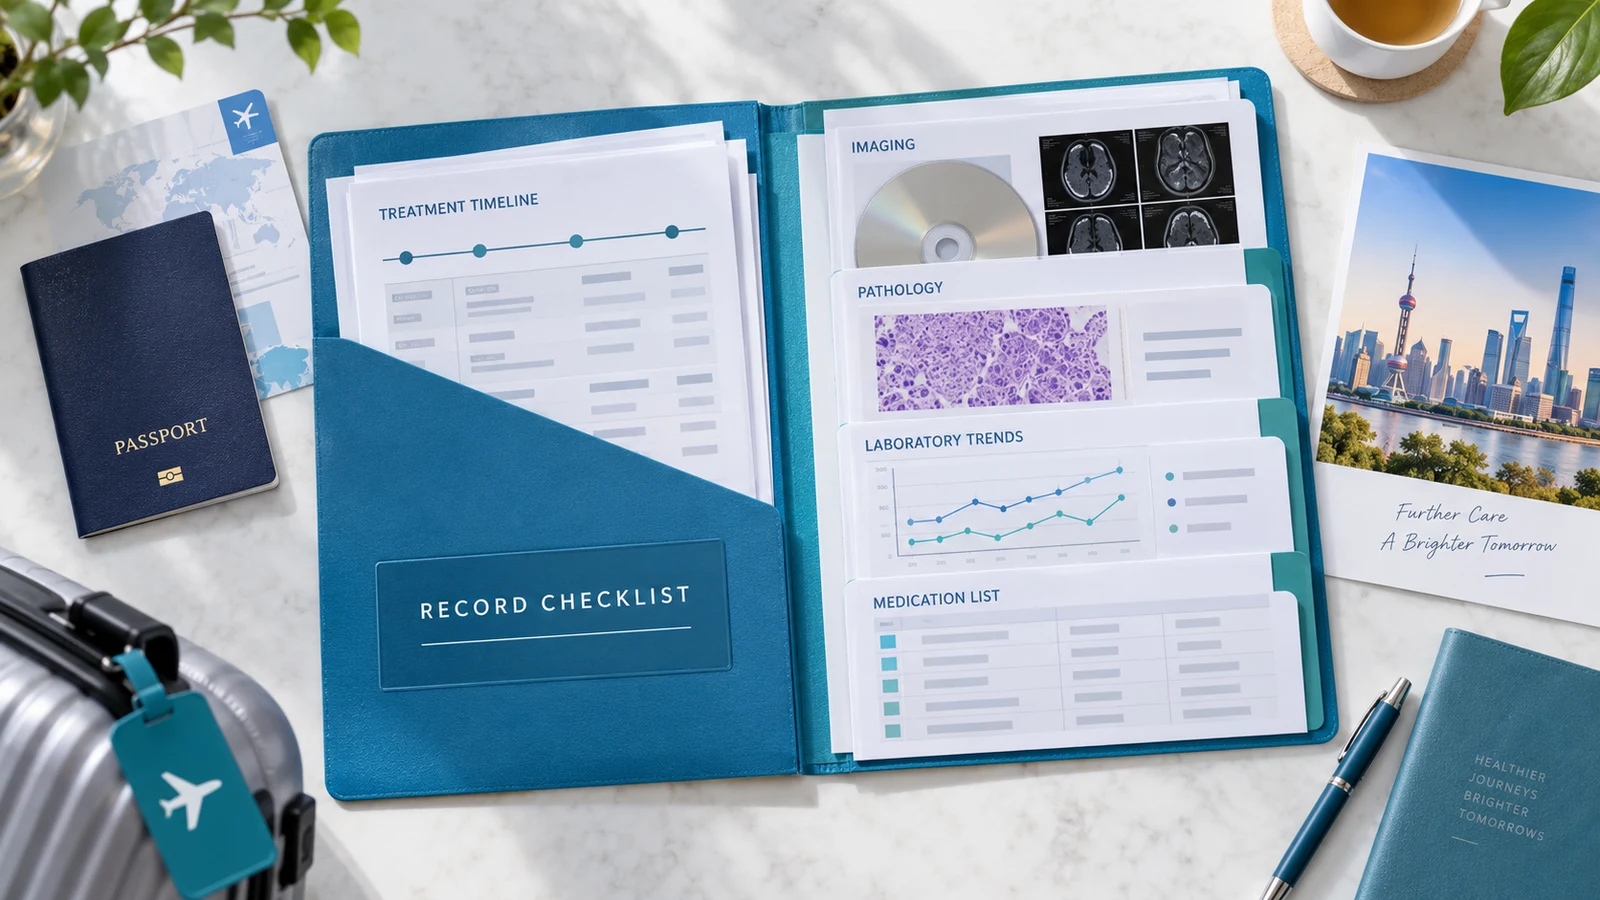
Create one folder with dated files and a one-page index. Keep the original-language versions as well as any translations. A practical core set includes the following.
1. Diagnosis and pathology documents
Include the original diagnostic pathology report and the most recent pathology report that documents suspected or confirmed recurrence. For lymphoma or leukemia, this may include biopsy reports, bone marrow reports, flow cytometry, cytogenetics, immunohistochemistry, molecular testing, or other disease-specific studies. For myeloma, it may include marrow results, serum and urine protein studies, free light chains, and relevant cytogenetic or molecular reports.
If tissue was collected recently, record where the specimen and slides are held. Do not ship tissue, slides, blocks, or blood samples internationally unless the treating institution and the receiving clinical service have provided instructions. Requirements for pathology review, sample transfer, import, and consent differ by institution and location.
2. CAR-T treatment record
Save the CAR-T discharge summary or treatment summary, including the intended target antigen, product or protocol name if available, leukapheresis date, lymphodepleting chemotherapy dates, infusion date, and the center that delivered care. Include manufacturing or trial documents only when they are appropriate to share and do not disclose another person's information.
The goal is not to prove access to a future product. It is to give clinicians an accurate account of what was given and when. A photo of a medication label alone is usually less useful than the complete treatment summary.
3. Response and relapse evidence
Put response assessments in chronological order. Examples may include PET/CT, CT, MRI, ultrasound, bone marrow examination, blood counts, disease-marker trends, and clinician notes describing symptoms or physical findings. Include the imaging report and, where available, the actual DICOM files or image-sharing link. Label each item with the date and reason for the test.
Keep both the last assessment showing response or stable disease and the first assessment raising concern for progression. The interval between them is context, not a treatment decision on its own.
4. Laboratory and infection history
CAR-T follow-up may involve blood-count changes, low immunoglobulin levels, and infection risk. Organize recent complete blood counts, kidney and liver function tests, inflammatory markers when available, microbiology results, transfusion history, immunoglobulin results, and infection-related admissions. Include vaccination records and a current medication list, especially antimicrobial prevention medicines and immune-supportive treatments.
This information helps a receiving clinical team understand recent safety issues. It does not tell a patient whether a particular therapy is safe or available.
5. Prior cancer treatment timeline
Prepare a plain-language timeline that lists diagnosis date, prior chemotherapy, radiation, transplant, antibody therapy, targeted therapy, cellular therapy, clinical-trial participation, major responses, and major complications. For each entry, include month/year, treatment name or regimen, number of cycles when known, reason it ended, and significant side effects.
The timeline is especially valuable when records come from more than one country. It helps a reviewing team ask focused questions without guessing which treatments came before or after CAR-T.
6. Current condition and practical information
Add the latest clinic note, medication list, allergy list, performance or mobility information if documented, transfusion needs, central-line information, and a short symptom summary written by the patient or caregiver. List the current oncologist and CAR-T center contact details, with permission to contact them if needed.
For travel planning, keep passport identity-page information and a preferred contact method in a separate administrative folder. Do not send passport scans, full medical records, or payment information through unsecured public channels.
Questions a Clinical Team May Need Answered
Different diseases require different evaluation. Instead of assuming what comes next, use your records to help clarify questions such as:
- What was the exact hematologic diagnosis and disease subtype before CAR-T?
- Which antigen did the CAR-T product target, and was target expression documented before treatment?
- What was the best response after infusion, and when was it assessed?
- What evidence currently suggests relapse or progression: symptoms, imaging, blood tests, marrow testing, biopsy, or another assessment?
- Has a new biopsy or other confirmation been considered by the treating team, and what is the reason for it?
- What infections, low blood counts, neurological effects, cytokine-release syndrome, or other complications occurred?
- What treatments and supportive medicines are being used now?
- Is the patient clinically stable enough to consider travel, according to the current treating team?
These are questions for the medical team, not a self-evaluation checklist. Some information may not be relevant to every person, and a clinician may request records not listed here.
How to Prepare Files for an International Discussion
Use clear filenames such as 2026-08-14_PET-CT_report.pdf rather than scan-final.pdf. Keep one PDF per document whenever possible, and avoid screenshots of multi-page records if a downloadable PDF is available. Do not edit the contents of medical reports. If you add a summary, label it clearly as a patient or caregiver summary.
If records are not in English or Chinese, retain the original document and add a careful translation of the key clinical sections. A translation should preserve dates, units, test names, medicine names, and uncertainty in the source record. It should not turn a suspected finding into a confirmed diagnosis. Some hospitals may require a specific translation format or a certified translation; confirm this directly when requested.
For imaging, ask the originating imaging department how to export studies in DICOM format and whether an access link is available. A radiology report is important, but it may not replace the underlying images when a specialist review is needed. Never assume a file will open on every system; check that the folder includes a viewer or clear download instructions if the original facility provides them.
Discussing Further Care in China
China has hematology and oncology services that see international patients, but the ability to assess a case depends on the records, current condition, local clinical processes, and whether a relevant service can review the situation. Submission of records does not mean that a patient can receive a specific medicine, cellular therapy, trial, hospital admission, or travel clearance.
MedToChina can help an international patient organize questions for a China-care discussion and identify missing information for a secure service conversation. This is communication support and does not assess the patient, recommend treatment, or decide treatment eligibility.
When speaking with a service team, ask practical questions: Which documents should be translated? Which files can be securely transferred? Are imaging files needed? Is there a current clinical note that should be included? What travel, language, and caregiver considerations should be prepared if an in-person visit becomes relevant? Keep treatment decisions with qualified clinicians who have reviewed the patient's situation.
A Simple 48-Hour Organization Plan
- Ask the current treating team for the latest clinical summary and urgent-care or travel advice.
- Download or request the pathology, CAR-T treatment summary, latest imaging reports and images, laboratory results, and medication list.
- Build a dated treatment timeline and a one-page index.
- Check that files open and that names do not expose unnecessary personal information.
- Keep original documents; add translations only as labeled companion files.
- Send records or questions through a secure, agreed channel rather than posting them publicly.
The purpose is to make a later clinical conversation more efficient, not to delay urgent local care or to decide treatment independently.
Frequently Asked Questions
Does relapse after CAR-T mean another CAR-T treatment is the next step?
Not necessarily. What may be considered after relapse depends on the cancer type, prior treatment, target biology, response history, current health, local regulations, and clinical judgment. This guide does not recommend a particular treatment.
Do I need a new biopsy after CAR-T relapse?
Only the treating clinical team can decide whether a biopsy or another test is needed. In some situations, clinicians consider imaging, biopsy, or other assessments to clarify suspected relapse, but the approach varies by disease and patient.
Should I send every medical record I have?
Start with the core record set and a clear timeline. A receiving team may request additional records. Keep the original files available and avoid sending highly sensitive identification or payment data unless a secure, requested process is in place.
Can MedToChina tell me whether I qualify for treatment in China?
No. MedToChina can receive records and questions through WhatsApp, identify missing information, and explain practical preparation steps. Treatment eligibility requires qualified clinical evaluation.
Can I travel to China while I am unwell after CAR-T?
Travel suitability must be discussed with the patient's current treating team. New fever, severe symptoms, infection concerns, bleeding, breathing problems, or neurological symptoms may need urgent local assessment.
Related MedToChina Resources
- CAR-T pre-screening record preparation
- Commercial CAR-T versus clinical trial pathways in China
- China-ready medical records checklist
- Investigational cancer drugs and trial pre-screening records
- Medical clearance before treatment in China
Send Your Records or Questions Through WhatsApp
If you are an international patient or caregiver considering a care discussion in China after CAR-T relapse, submit your information or send your medical-record questions through WhatsApp. Include a diagnosis summary, treatment timeline, current medicines, recent reports, travel period and practical questions. MedToChina can identify missing information and explain preparation steps for a service conversation.
Medical Disclaimer
This article is for general information only and is not medical advice, diagnosis, treatment advice, travel clearance, or a promise that a treatment, clinical trial, hospital service, or insurance outcome will be available. CAR-T relapse can involve urgent or complex clinical issues. Decisions about testing, treatment, medicines, and travel must be made with qualified clinicians who know the patient's condition. Seek urgent local medical care for concerning symptoms.
References
- National Cancer Institute. CAR T Cells: Engineering Patients' Immune Cells to Treat Their Cancers.
- Hashmi H, et al. ASTCT Committee on Practice Guidelines Survey on Evaluation and Management of Relapsed/Refractory Multiple Myeloma after Failure of Chimeric Antigen Receptor T Cell Therapy. Transplantation and Cellular Therapy. 2024;30(8):750-759.
- Dreyzin A, et al. Overcoming the challenges of primary resistance and relapse after CAR-T cell therapy. Expert Review of Hematology. 2024;20(7):745-763.
- Schroeder T, et al. Management of chimeric antigen receptor T (CAR-T) cell-associated toxicities. Intensive Care Medicine. 2024;50(9):1459-1469.
- Colton M, et al. Molecular Disease Monitoring in Patients With Relapsed/refractory B-Cell Lymphoma Receiving Anti-CD19 CAR T-Cell Therapy. Clinical Lymphoma Myeloma Leukemia. 2024;24(11):778-782.